Peak Physio Blog

20260604_122842-1-scaled.jpg

World Osteoporosis Day: Strong Bones Are Built, Not Inherited

Physio-led strength training for bone health at Peak Physio

An estimated 300,000 people in Ireland are living with osteoporosis, and many more are in the early stages without knowing it. Three in four adults over 50 are affected by low bone density in some form.

Most people first hear the word after a fracture. It doesn’t have to go that way. Around 80% of these fractures are preventable, and bone responds to what you ask of it at any age.

Being careful is not the answer


The instinct after a diagnosis is to be careful: lighter weights, gentler movement, avoid anything that feels risky. That’s the opposite of what bone needs. Bone is living tissue, and it gets stronger in response to real load. Walking and swimming are great for your heart, but neither asks enough of your skeleton to change bone density.

Done properly, with a programme built around what your body can safely handle, strength training is one of the few things proven to slow bone loss and improve balance. And balance matters just as much, because a fracture needs a fall before it needs weak bone.

Our Osteoporosis & Osteopenia Clinic


Led by Dan Delchev, our bone health specialist, the programme starts with a 45-minute one-to-one consultation: a full review of your history and goals, clear education on managing bone health safely, a walkthrough of the gym, and a plan to work from. If you’ve had a DEXA scan, we’ll go through your results with you. If you haven’t, we’ll advise you on getting one and use our own body composition testing in the meantime.

No referral needed, and no diagnosis needed either. Plenty of people come to us simply because bone health runs in the family.

€49 initial consultation

A 45-minute one-off session, with no obligation to continue. Claimable through VHI, Laya, Irish Life Health and GloHealth, and eligible for tax relief under Med 1.

Book your €49 consultation

What the LIFTMOR trial found


Researchers at Griffith University put postmenopausal women with low bone mass through high-intensity resistance and impact training: squats, deadlifts and overhead presses, properly supervised. Over the trial they recorded:

  • A 3.2% improvement in bone density at the lumbar spine
  • A 1.6% improvement at the femoral neck, the top of the hip
  • Measurable gains in strength and functional balance
  • No serious adverse events

Our bone health programme is built on this protocol. The key word is supervised: the trial worked because the loading was progressive and the technique was coached.

Bone health assessment at Peak Physio

Try this one at home: sit-to-stand, holding a weight

 
  1. Sit tall at the front of a sturdy chair, feet flat and hip-width apart.
  2. Hold a weight at your chest: a dumbbell, a kettlebell, or a bag of sugar to start.
  3. Stand up without using your hands, keeping your chest upright rather than rounding forward.
  4. Lower slowly back down. Do 3 sets of 8 to 10.

This is the everyday movement that keeps you independent, and loading it trains the hip and spine together. When 10 reps feel comfortable, add weight rather than reps. That added load is the part that counts.

Something bothering you?

Book online, or call us on (01) 667 0111. We’re in Ballsbridge and Trim.

Book an appointment

read more
EoinWorld Osteoporosis Day: Strong Bones Are Built, Not Inherited
running-pic.jpg

The Marathon Taper: Why Less Running Now Is the Right Call

With the Dublin Marathon on Sunday 25 October, you’re now in the taper. Your long runs come down, your weekly distance drops, and your legs finally get a chance to absorb everything you’ve put them through since the summer.

It’s also when most runners feel at their worst. Phantom aches appear, you feel sluggish, and you start to worry you’re losing fitness. None of that is a sign that something is wrong. It’s what happens when a body that’s used to being tired starts repairing itself.

The fitness is already banked


Nothing you do in the next three weeks will add to your fitness, but plenty could take away from it. The single biggest mistake we see is a panic long run ten days out. It won’t help on the day, and it’s more than enough to leave you sore at the start line.

So cut your distance, but keep some pace in your legs with a few short, faster efforts in your easy runs. Keep your strength work going, just lighter, and stop it entirely in the final week. Expect to sleep badly the night before, and don’t let it rattle you. The night two nights before is the one that counts.

Keep this one going: the single-leg glute bridge

Single-leg glute bridge exercise

  1. Lie on your back with one knee bent and that foot flat on the floor.
  2. Straighten the other leg and hold it in line with your thigh.
  3. Push through the planted heel and lift your hips, keeping them level.
  4. Lower slowly. Do 3 sets of 10 on each side.

Weak glutes are behind a lot of runner’s knee and hip pain, because the knee ends up controlling what the hip should be doing. If your hips drop or twist on one side, that’s the side to work on.

Your race week checklist

 
  • Nothing new: not the shoes, the socks, the gels or the breakfast.
  • Practise your race morning breakfast on your last couple of runs.
  • Walk around the expo as little as you can. Hours on your feet the day before add up.
  • Lay everything out the night before, pins included.
  • Plan your first 5km to feel too easy. It should.

Achilles or heel pain that won’t go away


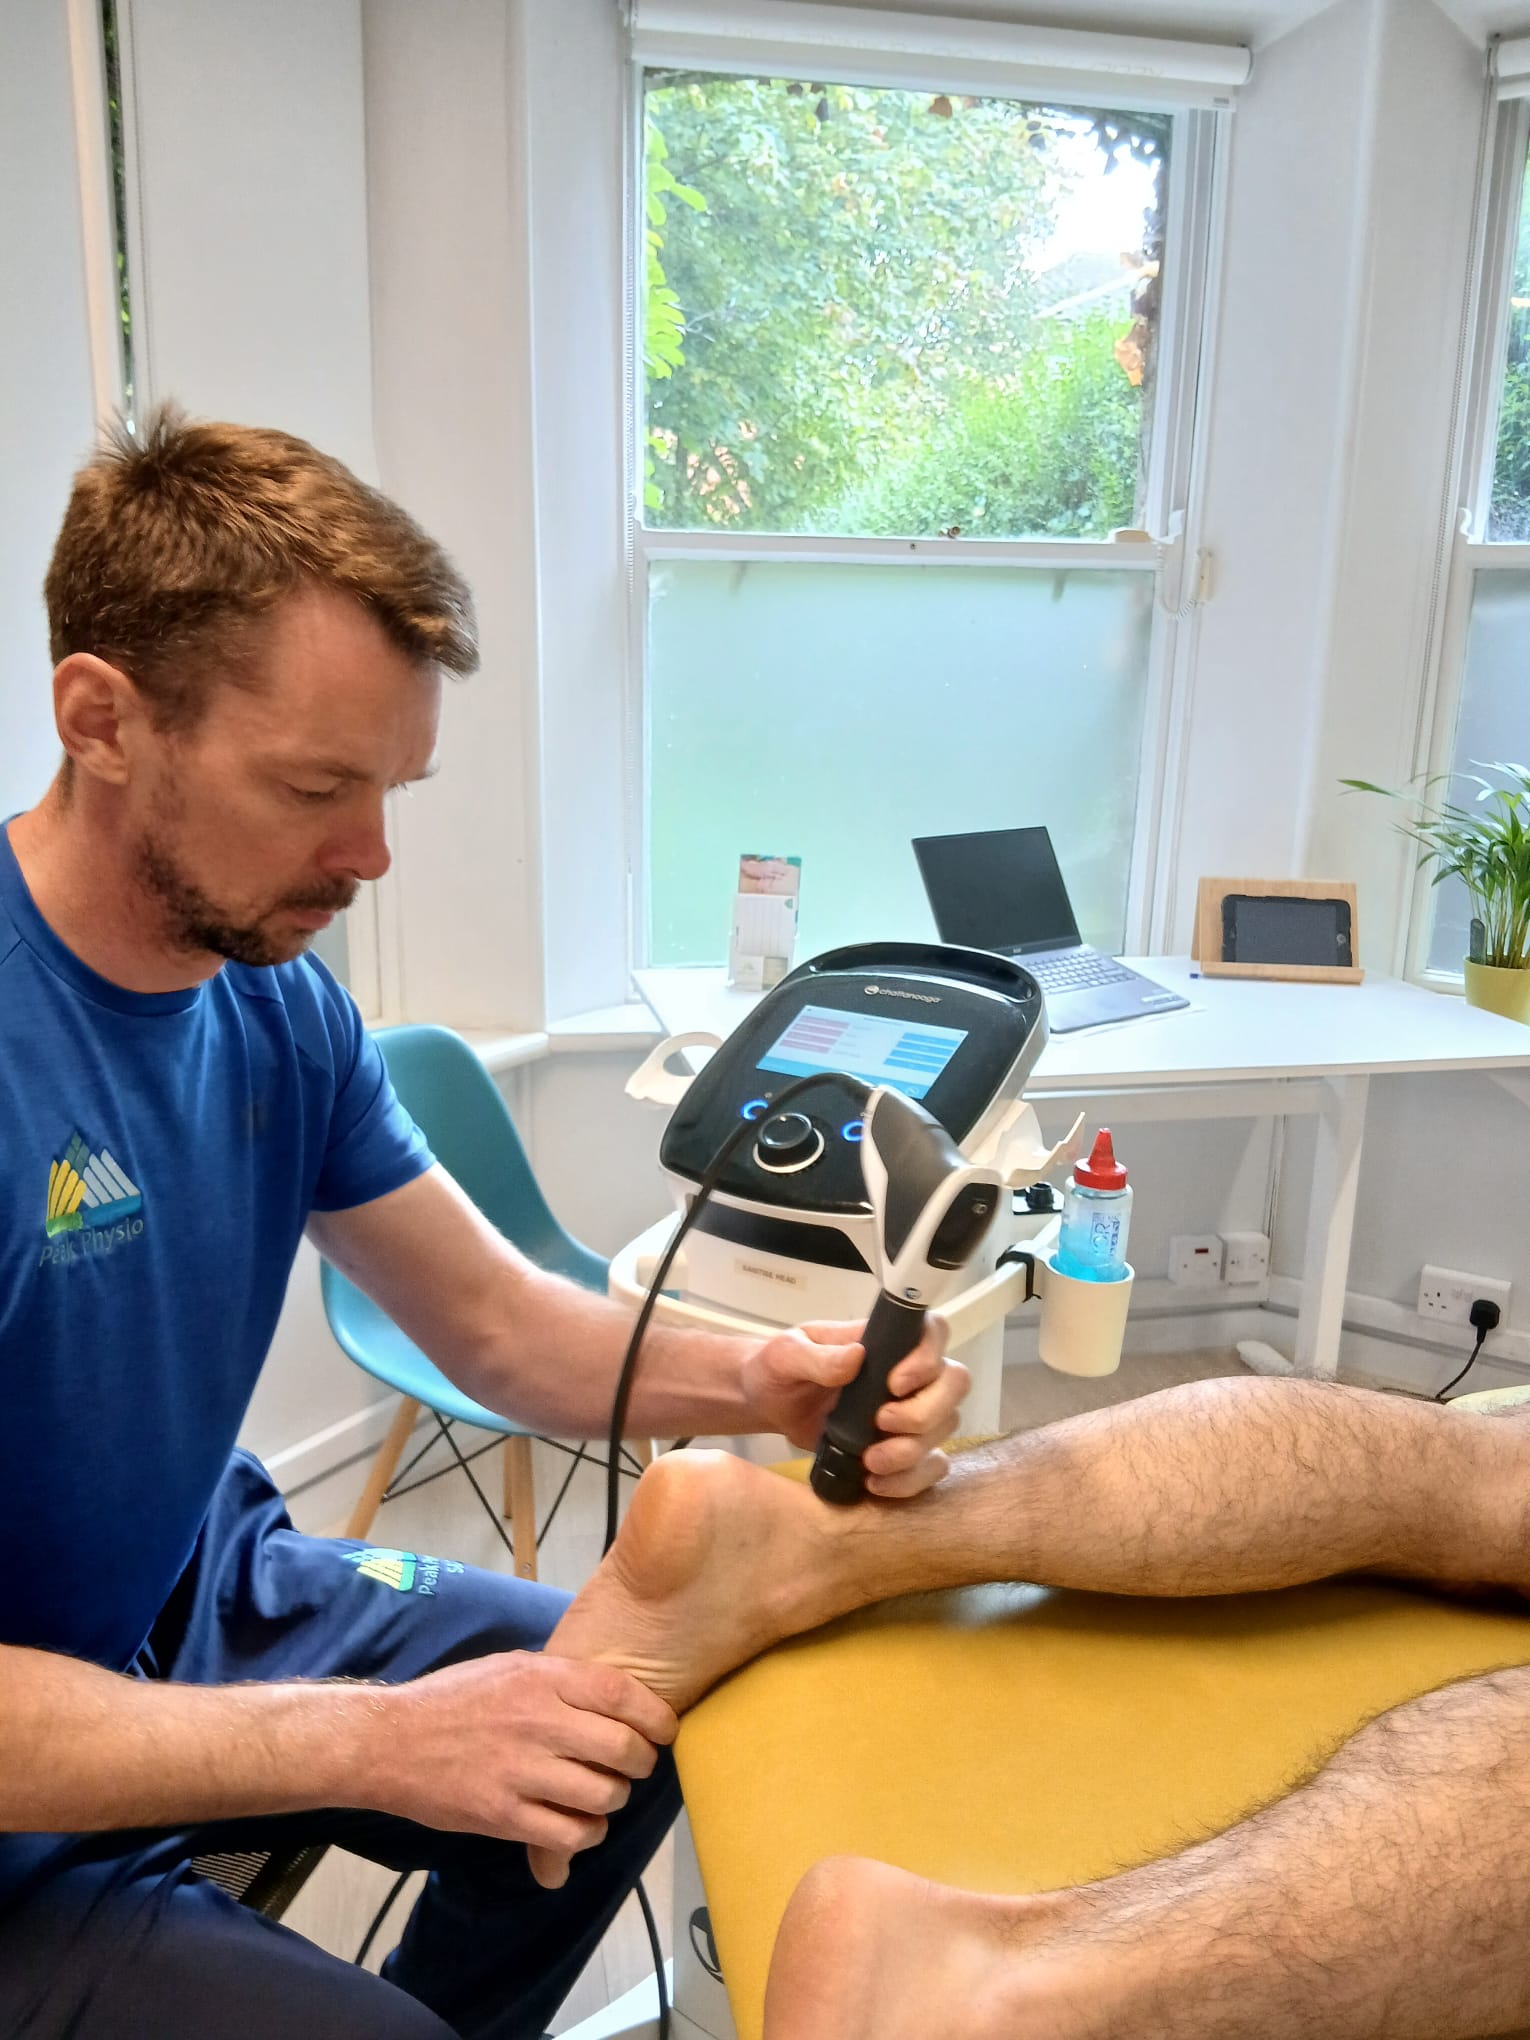
Shockwave therapy treatment for Achilles pain at Peak Physio

Tendon problems rarely settle with rest alone, and they’re one of our specialities. We use shockwave therapy alongside a loading plan, which means most runners keep running through treatment rather than stopping altogether. If a niggle has been with you for more than a few weeks, there’s still time before the 25th.

Something bothering you?

Book online, or call us on (01) 667 0111. We’re in Ballsbridge and Trim.

Book an appointment

read more
EoinThe Marathon Taper: Why Less Running Now Is the Right Call
dublin-marathon.gif

Dublin Marathon 2026: How to Get to the Start Line Injury-Free

The Irish Life Dublin Marathon is on Sunday 25 October. If you’re one of the 20,000-plus runners lining up, you’re in your biggest training weeks right now, and that’s exactly when we see most running injuries come through the door: sore Achilles, tight calves, and the knee that only hurts on the downhills.

It’s rarely one bad run. It’s usually a jump in weekly distance on legs that haven’t been strengthened for it. The good news is that most of these problems settle quickly if you catch them early.

Should you train through the pain?

A simple rule of thumb: pain up to about 3 out of 10 during a run, that has settled by the next morning, is generally fine to train through. Pain that climbs during the run, changes how you move, or is worse the next day is your cue to back off and get it checked.

Exercise 1: Single-leg calf raise

  1. Stand on one foot on the edge of a step, holding a rail for balance.
  2. Rise up onto your toes as high as you can.
  3. Lower slowly for three seconds, letting your heel drop below the step.
  4. Do 3 sets of 15 on each leg, then repeat with a slight bend in the knee.

Your calf takes several times your bodyweight with every stride. If you can’t manage 15 good reps, that’s worth knowing before race day.

Exercise 2: Foam rolling your calves, quads and glutes

  1. Sit or lie with the roller under the muscle, taking some weight through your hands.
  2. Roll slowly, about an inch a second, from one end of the muscle to the other.
  3. When you find a tender spot, pause there and breathe for 20 to 30 seconds.
  4. Spend 60 to 90 seconds on each area, after runs or on rest days.

Aim for a firm “good ache”, never sharp pain, and don’t roll directly on the Achilles or the side of the knee. Rolling eases tightness for a while, but it’s the strength work that makes the lasting difference.

The taper: don’t try anything new

Once your taper starts, resist the urge to squeeze in extra miles. Stick with the shoes, gels and breakfast you’ve trained with. Race day is not the day to try anything new.

Niggle that won’t settle?

Tendon problems are one of our specialities. We treat Achilles pain and heel pain using shockwave therapy alongside a loading plan, to keep runners running rather than stopping them altogether.

Book an appointment at our Ballsbridge or Trim clinic, or call us on (01) 667 0111.

read more
EoinDublin Marathon 2026: How to Get to the Start Line Injury-Free
Screenshot_20260415_144115_Chrome.jpg

Osteoprosis Focus: “DEXA vs. BIA: Which one should you use to track bone health in your 60s?”

DEXA vs. BIA: Which One Should You Use to Track Bone Health in Your 60s?

By Yordan Delchev, Senior Physiotherapist, MSc Sport & Exercise Medicine


If you’ve been told your bone density needs attention — or you’re simply being proactive about healthy ageing — you’ve likely come across two names: DEXA and BIA. Both are used to assess body composition, and both have a role in managing bone and muscle health. But they measure very different things, and understanding the distinction could genuinely change how you approach your health in your 60s and beyond.


What is DEXA?

DEXA (Dual-Energy X-ray Absorptiometry) is the clinical gold standard for measuring bone mineral density (BMD). It uses two low-dose X-ray beams to assess the density of bone tissue — most commonly at the lumbar spine and hip, which are the sites most vulnerable to osteoporotic fracture.

A DEXA scan produces a T-score, which compares your bone density to that of a healthy young adult. It’s the measurement your GP or consultant will use to diagnose osteopenia or osteoporosis, and to determine whether medication like bisphosphonates is warranted.

DEXA also provides a breakdown of lean mass and fat mass by body region — useful additional information, but not its primary purpose.

When DEXA is essential:

  • You’ve received a diagnosis of osteoporosis or osteopenia
  • You’ve had a fragility fracture (a break from a low-impact event)
  • Your GP has referred you for a bone health assessment
  • You’re on long-term corticosteroid medication
  • You’re post-menopausal and want a baseline measurement


What is BIA?

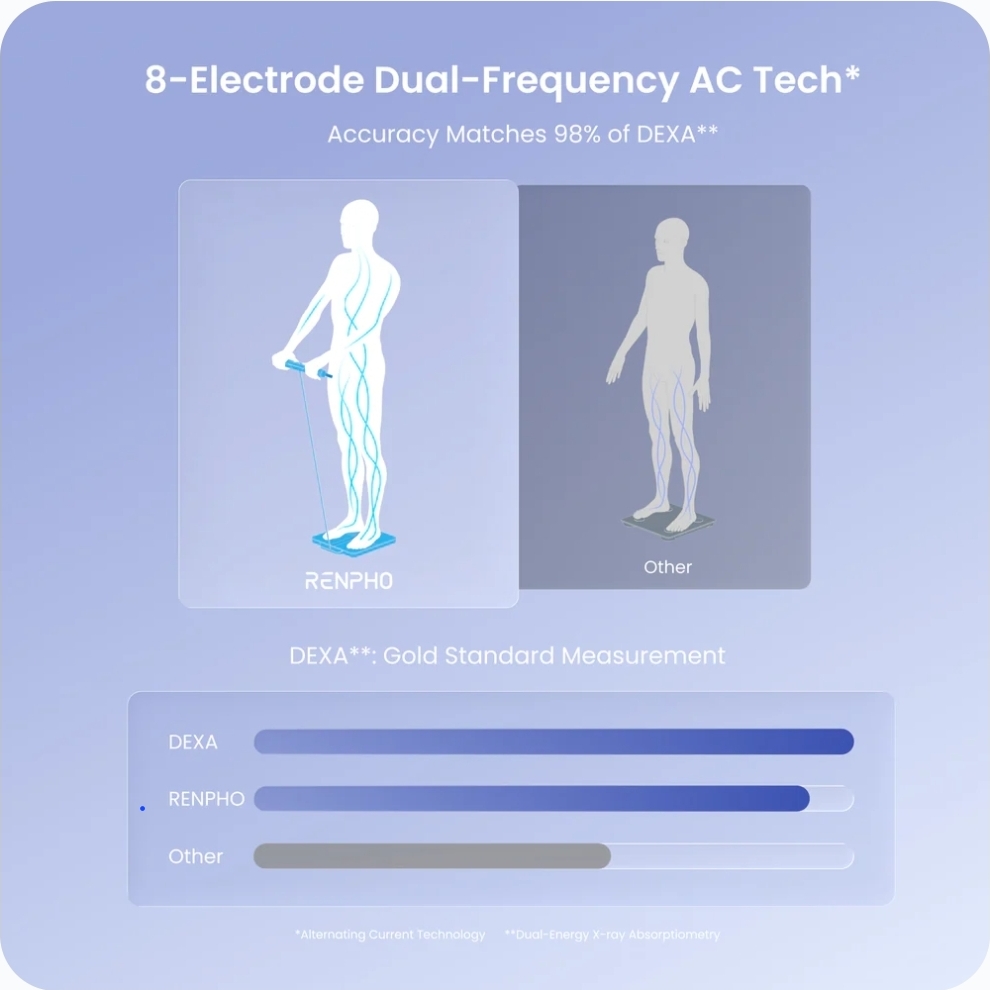
BIA (Bioelectrical Impedance Analysis) works on an entirely different principle. It passes a small, safe electrical current through the body and measures how it travels through different tissue types. Because muscle conducts electricity more readily than fat, BIA can estimate body composition — specifically muscle mass, fat mass, and body water.

Modern medical-grade BIA devices (including the one we use at Peak Physio) also estimate visceral fat, phase angle (a marker of cellular health), and skeletal muscle index — all of which are highly relevant to healthy ageing.

What BIA cannot do is measure bone density directly. It doesn’t produce a T-score and cannot diagnose osteoporosis.

Where BIA excels:

  • Tracking changes in muscle mass over time — critical for detecting and monitoring sarcopenia
  • Monitoring visceral fat, which is a key cardiovascular and metabolic risk marker
  • Assessing hydration status and cellular health
  • Frequent, low-cost monitoring (no radiation, no referral required)
  • Evaluating the impact of an exercise or nutrition programme on body composition

The Key Distinction: Bone vs. Muscle

This is the most important point to understand. In your 60s, you’re typically managing two parallel risks:

  1. Bone loss (osteoporosis / osteopenia) — the weakening of bone tissue
  2. Muscle loss (sarcopenia) — the gradual decline in skeletal muscle mass that accelerates after 50

These two conditions often coexist, and together they dramatically increase the risk of falls and fractures. But they require different tools to assess.

DEXA tells you about your bones. BIA tells you about your muscles. For a complete picture of your musculoskeletal health in your 60s, you arguably need both.


A Practical Framework

DEXA BIA
Measures Bone mineral density Muscle, fat, hydration
Diagnoses Osteoporosis / osteopenia Sarcopenia risk
Frequency Every 1–2 years (clinical) Every 8–12 weeks (monitoring)
Radiation Low dose None
Availability Hospital / clinic referral Available at Peak Physio
Cost Via GP / health insurance Included in our longevity assessments

Our Recommendation

If you haven’t had a DEXA scan and you’re in your 60s — particularly if you’re female, post-menopausal, or have risk factors for osteoporosis — speak to your GP about a referral. It’s the only way to get a definitive picture of your bone density, and many people don’t know they have significant bone loss until a fracture occurs.

At Peak Physio, we use medical-grade BIA as part of our Osteoporosis assessments to monitor muscle mass, track body composition changes, and guide your exercise programme over time. It’s a fast, painless, and highly informative tool — and when used alongside DEXA data, it gives us a genuinely comprehensive view of how your body is ageing.

The goal isn’t just avoiding fractures. It’s building a body that stays strong, resilient, and capable — for as long as possible.


Interested in a body composition assessment or Osteoporosis consultation? Book online at peakphysio.ie or call us to speak with Yordan directly.

read more
EoinOsteoprosis Focus: “DEXA vs. BIA: Which one should you use to track bone health in your 60s?”
taxes-740202_1920.jpg

Claim Your Medical Expenses

Claim Your Medical Expenses!

All major health insurers recognise care provided by Chartered Physiotherapists at Peak Physio.

To check your own cover, please review your own policy for its terms and conditions. We will provide receipts for all your treatment sessions either session by session or a full receipt of all visits at the end of  treatment depending on your preference.

If your health insurance provider does not cover you, you can also claim back some of your fees by claiming through your tax return form at the end of the year. To find out more click on the following link: How to claim health expenses

Below are some examples of the policies that are provided by different insurance companies:


                               Irish Life

Irish life covers both physiotherapy and acupuncture (depending on your own policy) and pre/post natal Pilates.

Physiotherapy:

Day to Day Plans cover physio – Depending on the plan

  • €25 back up – up to 5 visits
  • €30 x 3 visits
  • Physio visits covered 50% up to €25 x 8 visits each

Day to Day Business Plans:  Depending on the plan

  • €20 x 3 visits

Day to Day Health Plans: Depending on the plan

  • physio visits – 50% up to €30 x 25 visits each (subject to €50 excess)

Enhanced Health Plans: Depending on the plan

  • Money back on everyday medical expenses – physio sessions
  • Physio visits – €65 x 10 visits each

Acupuncture:

Acupuncture as part of Complementary Therapy:

  • €25 per visit x 3 visits.

Pilates:

Enhanced Maternity -Pilates Cover:

  • Pre/post natal Yoga & Pilates: €20 per visit x 2 visits


Please note that excesses may apply to some schemes. Please consult Irish Life Health to see what your Health Insurance policy will cover.

                                                       VHI                         

VHI covers both physiotherapy, acupuncture and Maternity Pilates(depending on your own policy) .

Physiotherapy:

One Plan Extra:

  • Physiotherapy cover – €25

Family Plan Plus Level 1:

  • Physiotherapy x 7 visits up to  €25 per visit

Healthsteps Gold:

  • Physiotherapy cover – x 7 visits up to €35 per visit

 One Plan Starter Day 2 Day

  • Physiotherapy x 3 visits at €20 per visit

Company Plan Extra Level 2 (Excess)

  • Physiotherapy 12 visits at €40 per visit


Acupuncture:

  • Acupuncture – x 7 visits up to €35 per visit


Pilates:

Maternity cover – baby bundle:

  • Maternity Pilates


Please note that excesses may apply to some schemes. Please consult VHI Health to see what your Health Insurance policy will cover.

VHI Healthcare

                            Laya Insurance                            

“At laya healthcare, our health insurance schemes provide cover for a variety of treatments. For example – physiotherapy, acupuncture, dietician and osteopathy. Please note, the therapist you attend for treatment must be a member of one of our recognised bodies before you’re eligible for benefit.”

All the below are only outlines, you must check with your health insurance policy or check with the health insurance company in regard to cover:

Physiotherapy:

Advantage Cover/Assure Cover/ Company Health:

  • Up to €20/€25 of physiotherapy visit is covered


Care Manage/Company Care/Connect Care:

  • 50 % cover of costs – up to 25 visits
  • 50-75% cover of costs – up to 25 visits

Control Suite:

  • Control 150 Create – up to €30 per visit – 25 visits
  • Control 150 Secure – up to €40 per visit – 25 visits
  • Control 150 total – up to €15 per visit – 25 visits


Acupuncture:


  • Control 300 total – Up to €15 per visit – 12 visits


  • Control 300 create – up to €30 per visit – 12 visits
  • Control 300 secure – up to €40 per visit – 12 visits


Please note that excesses may apply to some schemes. Please consult Laya Healthcare to see what your Health Insurance policy will cover.


read more
EoinClaim Your Medical Expenses

10 Thing’s You Didn’t Know About Tennis Elbow

10 things you didn’t know about Tennis Elbow

  1. The condition was initially described in 1873. The name “lawn tennis elbow” first came into use for the condition in 1882.
  2. Around 2 % of the population aged 30-50 will present with these symptoms.
  3. It is not just tennis players, Tennis Elbow is also known as Lateral Epicondylitis or Lateral Elbow Tendinopathy
  4. Our lateral elbow anatomy is made up of a number of components, the key component we have to assess when looking at Tennis elbow is our common wrist extensors. They create a broad tendon that inserts on the outside of the lower part of the humerus.
read more
Peak Physio10 Thing’s You Didn’t Know About Tennis Elbow

Achilles Tendinopathy – a common running injury

Running is an excellent way to get fit! However, sometimes when we start a new program we can feel little niggles beginning to arise. Achilles tendinopathy is a common injury among runners, especially those who are increasing their training load.

What is the achilles?

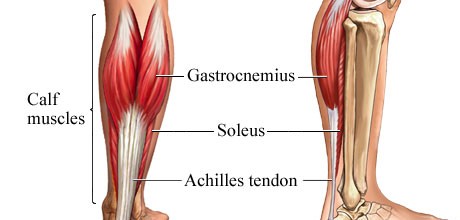
The achilles tendon is the biggest and strongest tendon in the body located in the back of the lower leg. The tendon has the capacity to resist large forces. It stems from the calf muscles (the gastrocnemius and soleus) and inserts into the heel of our foot (the calcaneus).

What is Achilles Tendinopathy?

A tendinopathy is a disorder which can happen when there is disrepair and disorganisation within the tendon structure. This can happen when there is excessive load placed on the structure, for example if someone starts running and increases their mileage too quickly.

The effects of overuse, poor circulation, lack of flexibility, gender, and hormonal factors can lead to tendinopathies. The structure of the tendon is disturbed by repetitive strain, causing inflammation. This cumulative microtrauma weakens the tendon, which ultimately leads to tendinopathy, especially if recovery is not allowed.

read more
Peak PhysioAchilles Tendinopathy – a common running injury
christmas-card-2945633_960_720.jpg

5 Tips to Keep Moving Over the Holidays!

2/3 of Irish adults are not getting enough exercise. All though Christmas is a time to switch off and relax, it’s important to try maintain a level of activity over the festive period. Here are easy tips to help keep you moving.

1. Walking
Weather permitting, try meet your friends and family for a nice walk instead of sitting by the fire. Aim to get up to your 10,000 steps daily.

2. Stretching
Going through a stretching regime is a nice way to get moving. Check out some good overall body stretching exercises here and here.

read more
Peak Physio5 Tips to Keep Moving Over the Holidays!
EoinPeak Physio Blog